
Revision summary
Alma-Ata (1978) and the Bhore Committee make community primary care the core of Health for All. Article 47 and the Eleventh Schedule place public health with the State and with panchayats. NRHM/NHM, ASHA, VHSNC and IPHS are the Indian local architecture; vacancies and weak honoraria undermine them. Ayushman Bharat Health and Wellness Centres must carry NCD and primary care, or insurance only pays late hospital bills. Untied local grants, filled PHCs, and a strong ASHA–ANM front door are the practical path.
Model answer
Copper italics in this answer — like this — are the key facts. Each one is unpacked in the Facts & figures rail.
Introduction
“Health for All” is not a tertiary-hospital slogan. The Alma-Ata Declaration, 1978, placed primary health care in the community, and the Bhore Committee, 1946, had already sketched a three-tier Indian system from village to district. India still loses mothers, newborns and TB patients in the last mile; that is why a local community intervention is a prerequisite, not an optional extra.
Body
Why the community level is the prerequisite
- Most illness is primary: fever, diarrhoea, pregnancy, hypertension, diabetes, mental distress, and injury. If the village and ward cannot treat or refer these, AIIMS-level capacity never reaches the person who needs it.
- Article 47 makes nutrition and public health a primary duty of the State; the Eleventh Schedule after the 73rd Amendment lists health and sanitation as panchayat functions. “Health for All” is therefore a local-government duty as well as a ministry programme.
- Distance, wage loss, and gender norms keep the poor from the district hospital; an ASHA, ANM and anganwadi in the habitation are the only staff who see the household every week.
- Outbreak control — polio rounds, Mission Indradhanush, and later COVID-style surveillance — worked when community workers and local bodies owned the list, not when a metro hospital issued a circular.
What India already built at that level
- Sub-centre, Primary Health Centre and Community Health Centre, with Indian Public Health Standards, are the official ladder; vacancies of doctors and staff nurses at PHC and CHC break the ladder.
- The National Rural Health Mission (2005), later the National Health Mission with an urban component, placed Accredited Social Health Activists, Village Health Sanitation and Nutrition Committees, and untied funds in the village.
- Janani Suraksha Yojana, Janani Shishu Suraksha Karyakram, and ICDS anganwadis show that maternal and child outcomes move when the intervention is local and cash-plus-care, not only a specialist wing.
- National Health Policy, 2017, shifted language toward comprehensive primary care and a larger public share of health spend.
- Ayushman Bharat, announced in the Union Budget 2018, has two arms: Health and Wellness Centres for expanded primary care (including non-communicable diseases) and a hospital-insurance arm. Without the first arm, insurance only pays for late admission.
What “appropriate” intervention means
- Appropriate is not a building named PHC; it is a package: medicines, diagnostics, a mid-level provider, referral transport, and community accountability through VHSNC and panchayat review.
- It includes nutrition, water, sanitation and vector control, because Article 47 and the Swachh Bharat mission affect diarrhoea and stunting more than an ICU does.
- Urban slums need the same logic through UPHCs and mahila arogya samitis; “community” is not only rural.
Gaps that still block Health for All
- Honorarium and career path of ASHAs remain weak; many States still treat them as volunteers for a national target.
- Specialist gaps at CHC dump cases back on the family; referral then dies.
- Commercial secondary care, without a strong public primary gate, produces both impoverishment and missed prevention.
Way forward
- Complete Health and Wellness Centres with a Community Health Officer, diagnostics and NCD drugs, and publish IPHS vacancy data by block.
- Route a larger untied health grant through panchayats and municipalities, with VHSNC social audit.
- Keep hospital insurance as a backstop, not as a substitute for the ASHA–ANM–PHC front door.
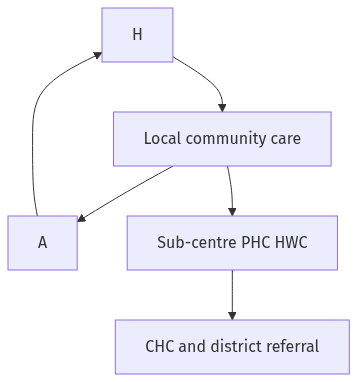
Flow diagram
Conclusion
- Health for All in India will be won or lost in the habitation: ASHA, sub-centre, PHC and the panchayat. National missions and insurance help only when that local community intervention is staffed, stocked and accountable, which is exactly what Alma-Ata and the Bhore design asked for.
Quick related
Students also ask
-
Professor Amartya Sen has advocated important reforms in the realms of primary education and primary health care. What are your suggestions to improve their status and performance?
Next question on this syllabus topic (2016 · Q9). View answer →
-
Can hospital insurance alone deliver Health for All?
No. Insurance pays for admission. Immunisation, antenatal care, hypertension and TB need a local worker and a stocked primary centre first.
-
Are panchayats legally linked to health?
Yes. The Eleventh Schedule lists health and sanitation. Many States still under-devolve staff and money, which is why the prerequisite is often missing.
Same topic · past papers
UPSC has asked this before
These previous-year questions sit on the same topic. Open one to practise the earlier ask.
-
2023 · Q1 · GS II · 10 marks
"Constitutionally guaranteed judicial independence is a prerequisite of democracy". Comment.
More from this topic
Q18 · UPSC Mains 2026 · GS II · 15 marks · Solution
Should education be treated primarily as a welfare obligation of the state or as a strategic investment for building a globally competitive, knowledge-driven nation? Critically evaluate.
Health, Education and Human Resources
Education is both a welfare duty and a strategic asset. The state must secure access, equity and foundational learning first, then build skills, universities and research. NEP 2020 tries to combine the two, but it needs higher spending, teacher capacity and accountability for learning outcomes.
Q7 · UPSC Mains 2026 · GS II · 10 marks · Solution
Malnutrition in India is not merely a public health concern; it is also a challenge of social equity, human development and effective welfare governance. Discuss.
Health, Education and Human Resources
• Public health: NFHS-5 shows stunting around 35.5 per cent, wasting 19.3 per cent and high anaemia among women and children. • Equity: malnutrition is higher among Scheduled Tribes, Scheduled Castes, poorer households and backward states. • Gender: early marriage, low food share and weak maternity support create an intergenerational cycle. • WASH link: unsafe water and sanitation cause infections that stop absorption of food. • Human capital: stunted children learn and earn less, reducing the demographic dividend. • Welfare: ICDS, Poshan 2.0, NFSA and PM POSHAN give scale but are cereal-heavy and unevenly delivered. • Governance: leakages, overloaded Anganwadi workers, weak convergence and data gaps limit impact. • Way ahead: first 1000 days, eggs and pulses, WASH convergence, reliable data, social audit.
Q17 · UPSC Mains 2024 · GS II · 15 marks · Solution
In a crucial domain like the public healthcare system, the Indian State should play a vital role to contain the adverse impact of marketization of the system. Suggest some measures through which the State can enhance the reach of public healthcare at the grassroots level.
Health, Education and Human Resources
Private-heavy care and out-of-pocket spend are the face of marketization in Indian health. Information asymmetry and cream-skimming make a pure market unsafe for the poor. Grassroots State role: Health and Wellness Centres, ASHA and ANM, district hospitals, public colleges, pooled drugs, ambulances. Insurance purchases care; it does not replace a public provider that sets a price floor. Article 47 and Article 21 emergency-care cases already treat basic health as a State duty. Capex on buildings is not enough; people who stay and drugs that exist are the reach.