
Revision summary
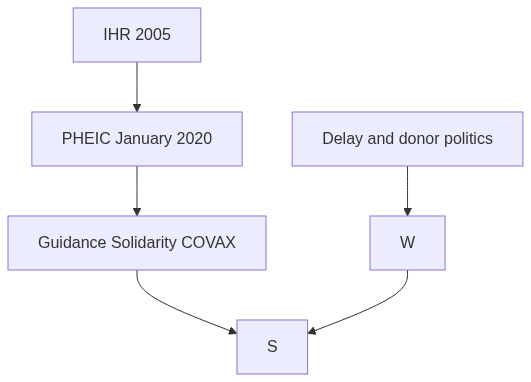
WHO’s COVID-19 role sits on IHR 2005: alert, PHEIC, and technical guidance. PHEIC on 30 January and pandemic on 11 March were late relative to spread. Solidarity trials, ACT-A and COVAX were the operational plus. Budget politics, China-related caution and Taiwan’s exclusion hurt independence. IHR cannot compel States; global health security is only as strong as members allow.
Model answer
Copper italics in this answer — like this — are the key facts. Each one is unpacked in the Facts & figures rail.
Introduction
The World Health Organization is the UN system’s health-security hub under the International Health Regulations, 2005. COVID-19 in 2020 was the hardest test of that mandate. WHO informed, convened, and later helped COVAX, but it was slow to name a public-health emergency, cautious on human-to-human spread, and structurally weak against great-power politics.
Body
Mandate and what WHO did
- IHR 2005 binds States to report public-health emergencies of international concern; WHO’s Director-General declares a PHEIC and issues temporary recommendations.
- WHO issued technical guidance on testing, clinical care, and later mask advice; it ran Solidarity trials and the Access to COVID-19 Tools accelerator with partners.
- COVAX was the equity vehicle for vaccines; WHO’s moral case for global health security is that a virus ignores borders.
- For developing States, WHO protocols were often the only public standard when bilateral science was noisy.
Critical failures in 2020
- The PHEIC came on 30 January 2020, after weeks of evidence; a pandemic was named only on 11 March. Delay cost preparedness.
- Early messaging tracked an information bottleneck around Wuhan and China; Taiwan’s exclusion from the WHO room became a political scandal of the year.
- The US notice of withdrawal (2020) showed that WHO’s budget dependence on assessed and voluntary funds lets a major donor punish the organisation mid-crisis.
- IHR has weak enforcement: WHO cannot compel a State to share samples, accept investigation, or keep trade measures proportionate.
Balanced examination
- WHO is a member-driven secretariat, not a world health police; blaming only Geneva hides State failure on PPE, lockdown timing, and vaccine nationalism.
- Global health security needed a faster alert, an independent origins probe, and a financed WHO that is not a hostage of one capital.
- Recommendation: strengthen IHR compliance, sustainable assessed contributions, and a pandemic treaty debate — the 2020 lesson, not the abandonment of WHO.
Flow diagram
Conclusion
WHO provided the only global operating system for COVID-19 guidance, trials, and vaccine equity talk, which is real health-security work. It failed on speed, independence from a major host State, and enforcement under IHR. A critical examination therefore reforms WHO; it does not pretend 2020 proved the organisation useless.
Quick related
Students also ask
-
National Education Policy 2020 is in conformity with the Sustainable Development Goal-4 (2030). It intends to restructure and reorient education system in India. Critically examine the statement.
Next question on this syllabus topic (2020 · Q18). View answer →
-
Could WHO have locked down China?
No. It has no army and weak IHR teeth. It can declare, recommend, and shame; States decide borders and lockdowns.
-
Should India leave WHO after 2020?
No. Reform and finance a more independent WHO. Exit would leave a vacuum that power politics would fill.
Same topic · past papers
UPSC has asked this before
These previous-year questions sit on the same topic. Open one to practise the earlier ask.
More from this topic
Q18 · UPSC Mains 2026 · GS II · 15 marks · Solution
Should education be treated primarily as a welfare obligation of the state or as a strategic investment for building a globally competitive, knowledge-driven nation? Critically evaluate.
Health, Education and Human Resources
Education is both a welfare duty and a strategic asset. The state must secure access, equity and foundational learning first, then build skills, universities and research. NEP 2020 tries to combine the two, but it needs higher spending, teacher capacity and accountability for learning outcomes.
Q7 · UPSC Mains 2026 · GS II · 10 marks · Solution
Malnutrition in India is not merely a public health concern; it is also a challenge of social equity, human development and effective welfare governance. Discuss.
Health, Education and Human Resources
• Public health: NFHS-5 shows stunting around 35.5 per cent, wasting 19.3 per cent and high anaemia among women and children. • Equity: malnutrition is higher among Scheduled Tribes, Scheduled Castes, poorer households and backward states. • Gender: early marriage, low food share and weak maternity support create an intergenerational cycle. • WASH link: unsafe water and sanitation cause infections that stop absorption of food. • Human capital: stunted children learn and earn less, reducing the demographic dividend. • Welfare: ICDS, Poshan 2.0, NFSA and PM POSHAN give scale but are cereal-heavy and unevenly delivered. • Governance: leakages, overloaded Anganwadi workers, weak convergence and data gaps limit impact. • Way ahead: first 1000 days, eggs and pulses, WASH convergence, reliable data, social audit.
Q17 · UPSC Mains 2024 · GS II · 15 marks · Solution
In a crucial domain like the public healthcare system, the Indian State should play a vital role to contain the adverse impact of marketization of the system. Suggest some measures through which the State can enhance the reach of public healthcare at the grassroots level.
Health, Education and Human Resources
Private-heavy care and out-of-pocket spend are the face of marketization in Indian health. Information asymmetry and cream-skimming make a pure market unsafe for the poor. Grassroots State role: Health and Wellness Centres, ASHA and ANM, district hospitals, public colleges, pooled drugs, ambulances. Insurance purchases care; it does not replace a public provider that sets a price floor. Article 47 and Article 21 emergency-care cases already treat basic health as a State duty. Capex on buildings is not enough; people who stay and drugs that exist are the reach.