
Revision summary
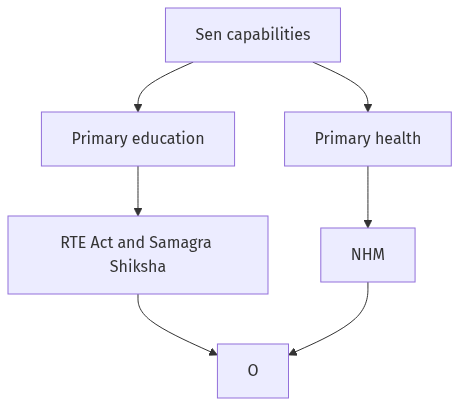
Sen treats primary education and primary health as capabilities that must come from public action, not only from growth. RTE, 2009, raised enrolment; the next reform is learning, teachers, ECCE and living School Management Committees. NHM and ASHAs expanded reach; the next reform is Health and Wellness Centres, a paid frontline cadre, and public-health—not only hospital insurance. ICDS, midday meals and school health should converge on the same child. Finance and audit must follow outcomes, which is the practical reading of Sen in Indian schemes.
Model answer
Copper italics in this answer — like this — are the key facts. Each one is unpacked in the Facts & figures rail.
Introduction
Amartya Sen treats literacy and basic health as capabilities that make other freedoms usable, not as leftover welfare after growth. India’s own data — high private spending on outpatient care, weak learning in government schools, and uneven primary health centres — show that enrolment and building counts are not enough. Suggestions must therefore change teaching, frontline health work, and public finance, using the laws and missions already on the books.
Body
Sen’s reform direction
- Sen has argued, with Jean Drèze and others, that India under-invests in elementary education and in primary health relative to its income, and that this drags down both growth and democracy.
- The capability view asks whether a child can actually read, and whether a woman can reach a functioning sub-centre, not only whether a school or a clinic exists on paper.
- That view fits Article 21A and the Right of Children to Free and Compulsory Education Act, 2009, and it fits the Directive Principles in Articles 39, 42, 45 and 47, including the State’s duty to improve nutrition and public health.
Primary education: status and suggestions
- The RTE Act, 2009, made eight years of schooling a right, with neighbourhood schools, pupil-teacher ratios, and 25 per cent seats in private unaided schools. Status is better on enrolment than on learning, as successive ASER-type findings have shown.
- Suggestion one: treat learning outcomes as the performance metric. Publish class-wise reading and arithmetic results at the cluster level, and use them in teacher support, not only in ranking States for political praise.
- Suggestion two: fill teacher vacancies and end multi-grade neglect in small schools; a right under the RTE Act is empty if one teacher covers several classes.
- Suggestion three: early childhood care under Article 45 and the National Early Childhood Care and Education Policy must join Class I, because primary failure often starts in an unprepared five-year-old. ICDS anganwadis need education-trained workers, not only supplementary nutrition.
- Suggestion four: Samagra Shiksha (which folded SSA and RMSA) should fund school libraries, special educators, and mother-tongue bridging in the first two years, instead of repeating civil-works saturation.
- Suggestion five: community monitoring through School Management Committees under the RTE Act must be real, with social audits of attendance and midday meals under the National Food Security Act, 2013, so the kitchen and the classroom both work.
Primary health care: status and suggestions
- National Rural Health Mission, later the National Health Mission, expanded ASHAs, Janani Suraksha Yojana, and public facilities, yet outpatient care is still heavily private and out-of-pocket.
- Suggestion one: make the Health and Wellness Centre under Ayushman Bharat a true first point of care with medicines, diagnostics, and a mid-level provider, so primary care is not a referral slip to a distant district hospital.
- Suggestion two: pay, train and legally protect ASHAs and ANMs as the permanent primary-care workforce; honorary volunteer status produces turnover and weak immunisation follow-up.
- Suggestion three: public health cadre and district epidemiology, not only insurance for hospitalisation. The National Health Policy, 2017, already points this way; hospital packages under PM-JAY cannot replace sub-centre work.
- Suggestion four: converge ICDS, NHM, and school health for nutrition, anaemia, and immunisation, because Sen’s “primary health” is a child’s growth chart as much as an adult’s OPD.
- Suggestion five: ring-fence State primary-health spending and fill MBBS and specialist gaps with bonded rural service that is actually served, plus telemedicine as a supplement, not as a substitute for a nurse at the village.
Shared governance suggestions
- Raise the public spend path toward the NHP target share of GDP, with a larger fraction on primary levels, which is Sen’s core fiscal point.
- Use outcome budgets and CAG performance audit of SSA/Samagra and NHM so implementation, not only allocation, is visible to the Public Accounts Committee.
- Do not privatise the first mile; use private providers where public capacity is absent, under publicly paid, quality-audited contracts, which keeps the capability in public responsibility.
Flow diagram
Conclusion
Sen’s case is that primary school and primary health are public capabilities, not residual charity. India has the RTE Act, ICDS, NHM and school-health missions; performance will rise when teachers teach, ASHAs are a real workforce, Health and Wellness Centres treat, and money is judged by learning and surviving children, not by buildings inaugurated.
Quick related
Students also ask
-
Public health system has limitation in providing universal health coverage. Do you think that private sector can help in bridging the gap? What other viable alternatives do you suggest?
Next question on this syllabus topic (2015 · Q12). View answer →
-
Did Sen ask only for more school buildings?
No. He stresses functioning schools and health centres that produce literacy and health. Buildings without teachers, medicines and accountability fail his test.
-
Can hospital insurance replace primary health care?
No. Insurance helps catastrophic hospital bills. Primary care is prevention, immunisation, maternity, and first treatment at the Health and Wellness Centre and sub-centre.
Same topic · past papers
UPSC has asked this before
These previous-year questions sit on the same topic. Open one to practise the earlier ask.
More from this topic
Q18 · UPSC Mains 2026 · GS II · 15 marks · Solution
Should education be treated primarily as a welfare obligation of the state or as a strategic investment for building a globally competitive, knowledge-driven nation? Critically evaluate.
Health, Education and Human Resources
Education is both a welfare duty and a strategic asset. The state must secure access, equity and foundational learning first, then build skills, universities and research. NEP 2020 tries to combine the two, but it needs higher spending, teacher capacity and accountability for learning outcomes.
Q7 · UPSC Mains 2026 · GS II · 10 marks · Solution
Malnutrition in India is not merely a public health concern; it is also a challenge of social equity, human development and effective welfare governance. Discuss.
Health, Education and Human Resources
• Public health: NFHS-5 shows stunting around 35.5 per cent, wasting 19.3 per cent and high anaemia among women and children. • Equity: malnutrition is higher among Scheduled Tribes, Scheduled Castes, poorer households and backward states. • Gender: early marriage, low food share and weak maternity support create an intergenerational cycle. • WASH link: unsafe water and sanitation cause infections that stop absorption of food. • Human capital: stunted children learn and earn less, reducing the demographic dividend. • Welfare: ICDS, Poshan 2.0, NFSA and PM POSHAN give scale but are cereal-heavy and unevenly delivered. • Governance: leakages, overloaded Anganwadi workers, weak convergence and data gaps limit impact. • Way ahead: first 1000 days, eggs and pulses, WASH convergence, reliable data, social audit.
Q17 · UPSC Mains 2024 · GS II · 15 marks · Solution
In a crucial domain like the public healthcare system, the Indian State should play a vital role to contain the adverse impact of marketization of the system. Suggest some measures through which the State can enhance the reach of public healthcare at the grassroots level.
Health, Education and Human Resources
Private-heavy care and out-of-pocket spend are the face of marketization in Indian health. Information asymmetry and cream-skimming make a pure market unsafe for the poor. Grassroots State role: Health and Wellness Centres, ASHA and ANM, district hospitals, public colleges, pooled drugs, ambulances. Insurance purchases care; it does not replace a public provider that sets a price floor. Article 47 and Article 21 emergency-care cases already treat basic health as a State duty. Capex on buildings is not enough; people who stay and drugs that exist are the reach.