
Revision summary
Private-heavy care and out-of-pocket spend are the face of marketization in Indian health. Information asymmetry and cream-skimming make a pure market unsafe for the poor. Grassroots State role: Health and Wellness Centres, ASHA and ANM, district hospitals, public colleges, pooled drugs, ambulances. Insurance purchases care; it does not replace a public provider that sets a price floor. Article 47 and Article 21 emergency-care cases already treat basic health as a State duty. Capex on buildings is not enough; people who stay and drugs that exist are the reach.
Model answer
Copper italics in this answer — like this — are the key facts. Each one is unpacked in the Facts & figures rail.
Introduction
India’s sick still pay out of pocket more than a republic should ask. Private beds and labs grew because the public core was thin, not because the market is a clinic of last resort. Marketization without a strong State means cream-skimming: paying patients inside, the poor outside or indebted. In healthcare the State is not a referee on the touchline. It is the team that must still play.
Body
Adverse impact of marketization
A free market in stents is a seller’s market.
- Peg: Private share of outpatient and inpatient care is high; catastrophic spend still pushes households below the line.
- Peg: Information asymmetry means the patient cannot shop for a procedure the way she shops for soap.
- Peg: Rural posts stay vacant while urban corporate hospitals cluster; clinical-establishment regulation is patchy.
- Peg: Insurance without public provision can inflate prices if the public hospital is too weak to be a price anchor.
Why the State must play
Article 47 and Article 21 already said the quiet part.
- Peg: Paschim Banga Khet Mazdoor Samity and Parmanand Katara treat timely emergency care as a State duty under Article 21.
- Peg: The grassroots right to a nurse, a drug and a referral is not a tradable.
- Peg: Market players can remain for electives; they cannot be the only competent bed in a district.
Grassroots measures
Provision first, purchase second.
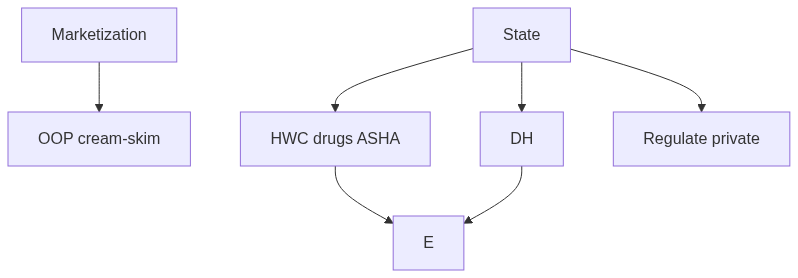
- Peg: Fill Health and Wellness Centres with diagnostics and drugs that do not require a private shop; pay ASHAs as the real primary-care network.
- Peg: Mid-level providers, served rural bonds, specialists at district hospitals, and public medical colleges attached to those hospitals expand seats and beds together.
- Peg: Immunisation, tuberculosis, vector control, mental health at the primary centre, ambulance grids, Jan Aushadhi and pooled procurement on the Tamil Nadu Medical Services model.
- Peg: Enforce clinical-establishment standards; audit insurance claims; steer volume to public facilities that are made fit — insurance as a servant of provision, not a substitute.
Flow diagram
Conclusion
Marketization without a public core prices the poor out and inflates the bill. The State enhances grassroots reach by staffing wellness centres and district hospitals, buying drugs in bulk, regulating private excess, and using insurance as a servant of provision — not a substitute.
Quick related
Students also ask
-
The crucial aspect of development process has been the inadequate attention paid to Human Resource Development in India. Suggest measures that can address this adequacy.
Next question on this syllabus topic (2023 · Q6). View answer →
-
Should the private sector be banned?
No. It should be regulated and not be the only competent bed in a district.
-
Is insurance the same as universal health?
Insurance is a payment channel. Universalism needs a provider the insured can actually walk into.
Same topic · past papers
UPSC has asked this before
These previous-year questions sit on the same topic. Open one to practise the earlier ask.
More from this topic
Q18 · UPSC Mains 2026 · GS II · 15 marks · Solution
Should education be treated primarily as a welfare obligation of the state or as a strategic investment for building a globally competitive, knowledge-driven nation? Critically evaluate.
Health, Education and Human Resources
Education in India balances a constitutional welfare duty with economic utility. Article 21A
Q7 · UPSC Mains 2026 · GS II · 10 marks · Solution
Malnutrition in India is not merely a public health concern; it is also a challenge of social equity, human development and effective welfare governance. Discuss.
Health, Education and Human Resources
• **Social Inequity:** Malnutrition heavily affects marginalised castes, tribal groups, and low-income households due to deep-rooted social stratification. • **Gender Bias:** Intra-household food discrimination and early motherhood create an intergenerational cycle of undernutrition for women and girls. • **Human Capital Loss:** Early childhood stunting causes irreversible cognitive damage, directly lowering educational outcomes and workforce productivity. • **Demographic Risk:** Without urgent nutritional interventions, India's demographic dividend risks turning into a socioeconomic liability. • **Governance Failures:** Administrative leakages in the Public Distribution System (PDS) and Integrated Child Development Services (ICDS) weaken last-mile delivery. • **Siloed Approach:** Poor coordination among health, sanitation, and rural development departments reduces the effectiveness of welfare schemes. • **Way Forward:** Success requires shifting from basic food security to nutritional justice through POSHAN Abhiyaan convergence and Article 21 rights.
Q11 · UPSC Mains 2024 · GS II · 15 marks · Solution
What are the aims and objects of recently passed and enforced, The Public Examination (prevention of Unfair Means) Act, 2024? Whether University/State Education Board examinations, too, are covered under the Act?
Health, Education and Human Resources
The Public Examinations (Prevention of Unfair Means) Act, 2024 targets organised leaks and unfair means in central public exams. Scheduled authorities include UPSC, SSC, Railway Recruitment Boards, IBPS and NTA; the Centre can add names. Offences are serious, including for service providers who handle papers. University and State board exams are not covered unless notified or a State copies the Act. The political spur was high-stakes testing in 2024; the legal scope remains the Schedule. The Act adds crime and punishment; cancellation of a paper remains an administrative and judicial decision.