
Revision summary
Holistic health means body, household, ecology and inequality together. Paradigms include hospitals, Alma-Ata primary care, AYUSH/ethnomedicine, and rights-based social determinants. COVID-19 exposed migrant invisibility, weak tribal PHCs, vaccine distrust and nutrition shock. Vertical hospital care without food and housing failed the poor. Assemble PHC, PDS, FRA livelihoods and non-discriminatory biomedical care; do not stop at a wellness slogan.
Model answer
Copper italics in this answer — like this — are the key facts. Each one is unpacked in the Facts & figures rail.
Introduction
Holistic health treats illness as body, household, ecology and inequality together. For marginalised sections — ST, SC, slum, migrant, PVTG — no single clinic model is enough. COVID-19 made that visible when the virus followed crowding, transport and distrust rather than a random medical map.
Body
Existing paradigms
Biomedical hospital care saves acute lives (oxygen, ICU) but is distant from hamlets and costly. During COVID-19, tertiary hospitals filled while tribal PHCs lacked oxygen and staff. Alma-Ata primary health care (1978) and India’s NRHM/NHM, ASHA and anganwadi are the public-health paradigm: prevention, immunisation, nutrition. They work when the worker is local and paid; they failed when migrants were invisible on lists.
AYUSH and tribal medicine are living systems (Elwin noted local healing; ethnomedicine is a syllabus topic). They can support care and meaning; they cannot replace oxygen. A holistic paradigm includes them without abandoning epidemiology.
Rights and structural paradigms (Xaxa, social determinants: land, food, water, caste clinic discrimination) say TB and stunting are political. WHO social determinants and Amartya Sen’s capability talk belong here. ICDS, PDS, POSHAN, PM-JANMAN are this paradigm in scheme form.
Community and PESA Gram Sabha health would make the hamlet the unit: quarantine decided with consent, MFP cash as nutrition, local language information. This was rare in 2020.
Inferences from COVID-19
- Migrant Adivasi and OBC workers walked home when industry shut: livelihood is health. Quarantine centres that ignored food taboos and menstrual needs failed. Vaccine uptake lagged where rumours met a history of coercive camps; trust is a clinical resource. Excess death in the poor was a class and crowding fact. Forest villages sometimes had fewer early cases (distance) then worse second-wave outcomes (no beds). Sickle-cell and TB co-morbidity in tribal belts were under-managed.
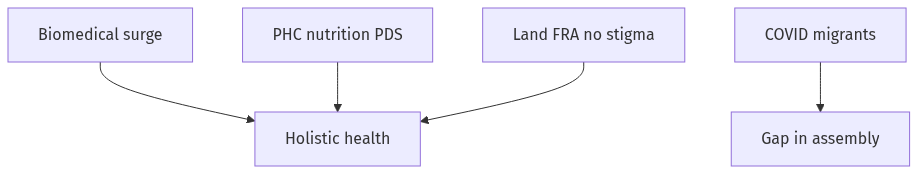
Holistic talk that only adds a yoga module to a corporate hospital is not holistic. Holistic health for the marginalised is PHC plus food plus FRA income plus non-discriminatory wards plus epidemic information in Ho, Santali, Gondi, Kui. COVID-19 showed that vertical disease control without social protection collapses.
Critical close
Do not romanticise “tribal immunity” or blame “superstition” as the main death cause. The paradigm that survived the pandemic is primary care + social determinants + respectful biomedical surge. Anthropology’s job is to keep the household and the hamlet in the protocol.
Flow diagram
Conclusion
Holistic health for the marginalised joins clinic, food, land and trust. COVID-19 proved that hospital modernity without migrant housing and hamlet PHCs is not holistic. Existing schemes name the parts; the pandemic showed they were not assembled.
Quick related
Students also ask
-
Elucidate the resurgence of ethno-nationalism from an anthropological lens.
Next question on this syllabus topic (2024 · Q7(c)). View answer →
-
Did traditional medicine fail during COVID-19?
It could not replace oxygen and vaccines. It remained part of meaning and minor care. A holistic system uses both epidemiology and local trust.
-
Were tribal areas spared?
Some were hit later, not spared. Distance delayed the first wave; the second wave and returning migrants closed that gap.
Same topic · past papers
UPSC has asked this before
These previous-year questions sit on the same topic. Open one to practise the earlier ask.
-
2022 · Q8(a) · Anthropology GS 2 · 20 marks
Compare the nature of tribal movements between North-East and Central India. Briefly mention the current status of existing tribal movements in these areas
More from this topic
Q6(a) · UPSC Mains 2026 · Anthropology GS 2 · 20 marks · Solution
Make a critical appraisal of the mesolithic culture of Ganga basin with reference to artifacts, faunal and human skeletal remains excavated from different sites
Evolution of the Indian Culture and Civilization
• Ganga basin Mesolithic sites like Sarai Nahar Rai, Mahadaha, and Damd
Q5(e) · UPSC Mains 2026 · Anthropology GS 2 · 10 marks · Solution
Contribution of L. K. Ananthakrishna Iyer in Anthropology.
Evolution of the Indian Culture and Civilization
L. K. Ananthakrishna Iyer is a pioneering figure in Indian anthropology, known for his monumental ethnographic surveys like The Cochin Tribes and Castes and The Mysore Tribes and Castes. Working during the colonial era, he bridged western anthropological methods with indigenous scholarship. His documentation of social stratification, material culture, and folklore laid the empirical foundation for Indian sociology and anthropology. Iyer also established the first department of anthropology in India at the University of Calcutta, shaping institutional teaching and research.
Q5(c) · UPSC Mains 2026 · Anthropology GS 2 · 10 marks · Solution
Article 371A of the Indian Constitution.
Evolution of the Indian Culture and Civilization
Article 371A of the Indian Constitution grants special autonomous status to Nagaland, protecting its traditional socio-religious practices, customary laws, and land ownership rights. Enacted via the 13th Constitutional Amendment Act, 1962, following the 16-point Agreement, it reflects the asymmetrical federal framework of India. The article places a special responsibility on the Governor regarding law and order and regional financial allocations. It balances tribal autonomy with national integration, though it faces implementation challenges in modern governance.